Cardiac Screening After 40: Which Tests Actually Matter
Turn 40 in India and the health check-up industry comes calling, with packages promising 70, 90, even 120 tests, many of questionable value. Meanwhile the tests that actually catch heart disease early get lost in the noise. Cardiovascular disease remains India’s biggest killer, and much of it is preventable if risk is found in time. The trouble is not too little testing but undiscerning testing: money spent on exotic scans while blood pressure, sugar and lipids go unmeasured. This guide cuts through the package marketing to the screening that evidence actually supports after 40.
The non-negotiable core: know your numbers
Four measurements carry most of the predictive power, and all are cheap. Blood pressure, taken properly after rest, identifies hypertension, the silent driver of strokes and heart failure. Fasting blood sugar and HbA1c reveal diabetes and pre-diabetes, which ravage arteries years before symptoms. A fasting lipid profile, total cholesterol, LDL, HDL and triglycerides, maps the cholesterol risk, and Indians should add lipoprotein(a) once, since it runs high in South Asians and is genetically fixed. Waist circumference and BMI capture the thin-fat risk that BMI alone misses. These five, repeated every one to two years, or more often if abnormal, form the foundation. Anyone selling you a cardiac package without centring these is selling decoration.
Which heart-specific tests matter?
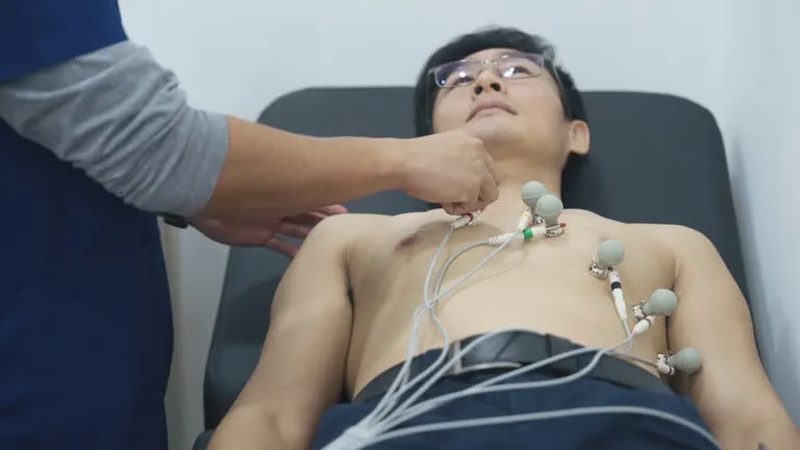
Beyond the basics, a resting ECG is a reasonable baseline after 40: cheap, quick, and useful for comparison later, though a normal ECG does not rule out disease. An echocardiogram, an ultrasound of the heart, is valuable if there are symptoms, murmurs, hypertension or family history, showing pumping strength and valve function. For asymptomatic people at elevated risk, a coronary calcium scan (CT) can refine decisions: a zero score is reassuring, while significant calcium argues for aggressive prevention. Stress testing, treadmill or stress echo, is best reserved for those with symptoms or high risk, not as routine screening, since false positives in low-risk people cause more harm than good. hs-CRP, a marker of inflammation, can help borderline cases. Kidney function and urine protein tests matter because the kidneys and heart fail together.
Tests you can probably skip
Whole-body CT or MRI scans marketed to the healthy are the classic oversell: they find incidental nodules that trigger anxiety, biopsies and cost, while missing the actual risks. Routine angiography or CT coronary angiography in asymptomatic low-risk people is not recommended by any major guideline. Fancy vitamin panels, food intolerance tests and full-body tumour marker screens bundled into executive packages have poor evidence as screening tools. Genetic testing for heart risk has niche uses, such as suspected familial hypercholesterolaemia, but is not a general screen. Money saved here is better spent on the basics done regularly, or on a dietitian and gym membership.
How often should you screen?
For healthy adults over 40, the core numbers, blood pressure, sugar, lipids, deserve checking every one to two years; annually if any are borderline or if you have diabetes, hypertension or a strong family history. An ECG every couple of years provides a useful baseline. After 50, or earlier with risk factors, discuss a coronary calcium scan with your doctor as a one-time risk refiner. People with established disease follow their cardiologist’s schedule, which is tighter. The key principle: screening is a rhythm, not an event. A single grand check-up at 45 followed by a decade of neglect is worth less than modest tests done faithfully.
Making screening lead to action
A test only matters if its result changes behaviour. Borderline sugar should trigger diet and exercise change, not watchful waiting. High LDL in a high-risk person should prompt a statin discussion, not a supplement experiment. Hypertension needs treatment, not just monitoring. Keep your own records: a simple file or app with yearly numbers reveals trends that single readings hide. And remember that screening complements, never replaces, the daily work: not smoking, moving, eating sensibly, sleeping enough and managing stress do more than any scan. The best screening programme is the one whose results you actually act on.
FAQs
Are executive health packages worth it? They can be convenient, but cherry-pick the evidence-based components and ignore the filler; an annual package never substitutes for acting on results.
Should I get a CT calcium scan at 40? Discuss it if you have intermediate risk or family history; it is most useful for refining decisions in borderline cases, less so at very low or very high risk.
Does a normal ECG mean my heart is fine? No. An ECG can be normal in significant coronary disease; it is one piece of the puzzle, not a clean chit.
Cardiac screening after 40 is not about the most tests but the right tests, repeated faithfully and acted upon honestly. Blood pressure, sugar, lipids, waist, an ECG baseline and selective deeper dives: this lean panel catches the risks that kill, without the noise that merely bills.
Compiled by the Khabar 24h Editorial Desk from publicly available sources.
Related stories
View all →
Single-Dose In Vivo CAR-T Shows 90% Response in Myeloma Trial
An experimental cancer therapy that turns a patient’s own cells into treatment inside the body has shown a 90% response rate in…

Punjab Drug Crisis Takes Centre Stage Ahead of 2027 Polls
Punjab's drug crisis dominates debate ahead of the 2027 polls, with the BJP, SAD, AAP and Congress all making it a key…

West Bengal Orders FIRs Over Missing Covid Equipment
West Bengal has ordered FIRs after medical equipment bought during the Covid-19 pandemic was found missing at 64 health centres across the…

Khabar 24h Editorial Desk — our explainers are prepared by the Khabar 24h editorial team using AI-assisted research tools, and every piece is reviewed by a human editor before publishing. We do not claim original reporting: our work is turning complex topics into simple, accurate summaries. Spotted an error? Write to contact@khabar24h.com — our corrections policy aims for same-day review.
More from this author →